Cart is empty
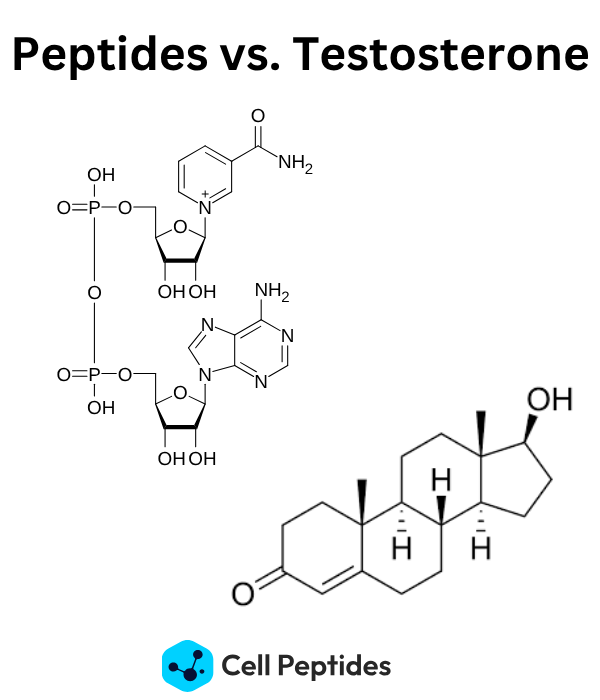
Many people are curious about the difference between peptides and testosterone when it comes to muscle growth, and the two work very differently. Testosterone supplementation provides a hormone from outside the body.
Growth hormone (GH) peptides prompt your own system to release more of its own native GH. In this article, we compare the mechanism, evidence, and research context for peptides vs testosterone.
What Is the Core Difference Between Peptides and Testosterone?
Remove the labels and it comes down to one question: Does the compound replace a hormone, or trigger the body to make more of its own?
Testosterone is exogenous, meaning you administer it, and it then attaches to hormone receptors [1] in muscle tissue, which stimulates protein synthesis along with better nitrogen retention. The problem with this approach is feedback. When exogenous testosterone is present, the body [2] detects the elevated levels and reduces its own output. [3]. In most countries, testosterone requires a prescription, and in the United States it is a Schedule III controlled substance [4].
Growth hormone secretagogue peptides take the opposite path. Compounds such as CJC-1295, Ipamorelin, and GHRP-6 trigger the pituitary gland to release more of your own GH and, further down, insulin growth factor 1 (IGF-1). These peptides do not bind to the hormone receptor at all. They also tend to leave natural production intact rather than suppressing it. In legal terms, such peptides are research compounds in most jurisdictions, and they remain banned in tested sports. The main difference between the two, replacing a hormone versus stimulating one, underlies almost every other contrast in this article.
How Each Works: Mechanism Comparison
Testosterone: the androgen receptor pathway
Testosterone enters the muscle cell and attaches to the androgen receptor inside the cell nucleus. That receptor stimulates gene transcription, increasing protein synthesis, improving nitrogen retention, and helping activate the dormant satellite cells associated with muscle fiber repair and growth. A portion of circulating testosterone is also converted to estradiol [5], and that estradiol tends to support recovery rather than work against it. However, there is a cost. As your androgen levels rise, luteinizing hormone and follicle stimulating hormone fall, and your own testosterone output stops for as long as dosing continues.
GH secretagogue peptides: the GH/IGF-1 axis
The peptide side works differently. CJC-1295 w/ DAC , Ipamorelin and GHRP-6 act on the pituitary gland, not on muscle cells. They trigger a GH pulse, which drives the liver to release IGF-1 [6], and IGF-1 then binds to its receptor in muscle to initiate protein synthesis [7]. This first step has solid human evidence from research. In healthy adults, a single dose of CJC-1295 increased growth hormone levels for about 6 days and IGF-1 levels for 9 to 11 days [8]. Ipamorelin is known for its selectivity, which means it releases growth hormone without the accompanying cortisol or prolactin increase seen with older peptides [9]. Given that this process does not involve the androgen receptor, both peptides and testosterone can be used in the same individual.
IGF-1 analogs (PEG-MGF): the direct IGF-1 pathway
PEG MGF works further downstream. Rather than waiting for a growth hormone pulse, PEG-MGF acts on muscle IGF-1 receptors more directly. With this compound, we are most interested in activating dormant satellite cells after muscle damage, representing the early proliferation phase that comes before muscle repair [10]. However, most of the evidence on this is preclinical or in vitro (not in animals or humans), and at least one independent group could not activate the satellite cells, so this issue is far from settled.
| Research note. Testosterone and GH peptides act on entirely different receptor systems. In research, they are often studied as complementary rather than competing variables. |
Research Evidence Comparison
Testosterone use has decades of human clinical data behind it. The landmark study came from Bhasin and colleagues, whose trial gave healthy men 600 mg of testosterone enanthate weekly and recorded gains in fat-free mass and strength, with and without training. A later study established a dose-response pattern based on increasing doses. [11]. Testosterone has received FDA approval for hypogonadism, so its safety and efficacy record is unusually well-studied for a muscle-relevant compound. The downsides are just as well documented: 1) hypothalamic-pituitary-testicular axis (HPTA) suppression, which shuts down your body’s natural hormone production, 2) an increase in hematocrit, and 3) male hormone effects [12].
The peptide side has less research data in humans, and direct performance data is limited compared to testosterone. There are firm reference points, though. Sermorelin and tesamorelin are both growth hormone release hormone (GHRH)-based and have FDA approval, and tesamorelin has randomized trial data showing about a 15 percent drop in visceral fat versus placebo, along with higher IGF-1 levels [13].
The reported side effects are milder, with no male hormone effects and no shutdown of natural hormone production. In practice, testosterone is the better understood compound, and the GH peptides are the easier ones to obtain for use. If you are weighing peptides vs testosterone for muscle growth, the difference in evidence and risks is the real decision point, not raw potency.
Key Differences at a Glance
Here is the comparison in one view. Each row is a factor researchers tend to weigh, with the two classes kept side by side.
| Factor | Testosterone | GH secretagogue peptides |
|---|---|---|
| Mechanism | Androgen receptor | GH / IGF-1 axis |
| Hormone type | Exogenous (replacement) | Endogenous stimulation |
| HPTA suppression | Yes | No |
| Human evidence | Extensive | Limited, growing |
| FDA approval | Yes (hypogonadism) | No (performance use) |
| Legal status (US) | Schedule III controlled | Research compound |
| WADA status | Prohibited | Prohibited |
| Side effect profile | Well characterized | Less established |
| Androgen-related effects | Yes | No |
Which Is More Relevant for Muscle Growth?
There is no universal winner here, only an answer that depends on what you are trying to achieve.
If your goal is androgen-driven muscle hypertrophy, testosterone is the reference compound, and nothing else has as much human evidence behind it. If your focus is on growth hormone stimulation, recovery initiation, or the IGF-1 pathway, GH secretagogue peptides are the natural tools. In addition, their research status is more accessible, since they are not controlled substances in most regions. For body recomposition, where muscle and fat matter simultaneously, GH peptides offer a second mechanism: growth hormone also drives lipolysis, the release of stored fat [14, 15]. For combination work, the 2 behave independently by design, working through completely separate pathways. In other words, the question is rarely which is stronger, but which pathway your goals employ.
Safety & Regulatory Notice
Testosterone is a controlled substance and possessing it without a prescription is illegal in most countries. GH peptides are research compounds: legal to buy for laboratory use, but not for personal performance enhancement. Both testosterone and GH secretagogues appear on the WADA Prohibited List, so neither is permitted in tested sports [16]. Neither belongs outside an approved medical or research setting.
Conclusion
The short version: testosterone and peptides are not 2 routes to the same destination. They use completely different pathways. Testosterone has a stronger human evidence base, while GH peptides offer GH axis stimulation with no male hormone receptor involvement and no natural hormone suppression. For the compounds covered here, browse our bodybuilding peptide collection, and for a wider survey see our roundup of the best peptides for muscle growth.
FAQs
Are peptides better than testosterone for muscle growth?
Better is the wrong question, since the 2 are used for different goals. Testosterone has more human evidence for a direct anabolic effect. GH peptides are active in the growth hormone axis and recovery pathways, without androgenic activity. So for you, the right pick depends on the mechanism you want to isolate.
Can peptides be used alongside testosterone?
Yes, and they often are. Given that GH secretagogues and testosterone act through separate receptor systems, they function independently, which is exactly why some protocols include both rather than one or the other.
Do peptides increase testosterone levels?
GH secretagogues such as CJC-1295 and Ipamorelin act on the growth hormone axis, not the androgen system, so they do not raise testosterone directly. A separate group of peptides, the GnRH-type compounds, can influence testosterone levels, but those are in a different category from the GH peptides discussed in this article.
Are peptides safer than testosterone for research?
The side effect profile of GH peptides tends to be milder, with no natural hormone suppression and no male hormone effects. However, the human safety record for testosterone is far more established. Each has different risk profiles, and that is the most important way to think about it.
References
[1] Androgen receptor (Wikipedia) – https://en.wikipedia.org/wiki/Androgen_receptor
[2] Bhasin S, et al. The effects of supraphysiologic doses of testosterone on muscle size and strength in normal men (PubMed) – https://pubmed.ncbi.nlm.nih.gov/8637535/
[3] Hypothalamic-pituitary-gonadal axis (Wikipedia) – https://en.wikipedia.org/wiki/Hypothalamic%E2%80%93pituitary%E2%80%93gonadal_axis
[4] Suppression of spermatogenesis by exogenous testosterone (PubMed) – https://pubmed.ncbi.nlm.nih.gov/33292112/
[5] DEA Drug Fact Sheet: Steroids, Schedule III controlled substances – https://www.dea.gov/sites/default/files/2020-06/Steroids-2020_0.pdf
[6] Aromatase (Wikipedia) – https://en.wikipedia.org/wiki/Aromatase
[7] Insulin-like growth factor 1 (Wikipedia) – https://en.wikipedia.org/wiki/Insulin-like_growth_factor_1
[8] Mechanisms of IGF-1-mediated regulation of skeletal muscle hypertrophy and atrophy (PMC) – https://pmc.ncbi.nlm.nih.gov/articles/PMC7564605/
[9] Teichman S, et al. Prolonged stimulation of GH and IGF-1 secretion by CJC-1295 in healthy adults (PubMed) – https://pubmed.ncbi.nlm.nih.gov/16352683/
[10 ]Raun K, et al. Ipamorelin, the first selective growth hormone secretagogue (PubMed) – https://pubmed.ncbi.nlm.nih.gov/9849822/
[11] Muscle satellite (stem) cell activation during local tissue injury and repair (PMC) – https://pmc.ncbi.nlm.nih.gov/articles/PMC1571137/
[12] Bhasin S, et al. Testosterone dose-response relationships in healthy young men (PubMed) – https://pubmed.ncbi.nlm.nih.gov/11701431/
[13] Suppression of spermatogenesis caused by TRT and anabolic-androgenic steroids (PMC) – https://pmc.ncbi.nlm.nih.gov/articles/PMC9243576/
[14] Tesamorelin in HIV-associated lipodystrophy: meta-analysis of randomized controlled trials (PubMed) – https://pubmed.ncbi.nlm.nih.gov/41545261/
[15] The effects of growth hormone on adipose tissue: old observations, new mechanisms (PMC) – https://pmc.ncbi.nlm.nih.gov/articles/PMC7180987/
[16] WADA Prohibited List – https://www.wada-ama.org/en/prohibited-list