Cart is empty

Cagrilintide (you can buy Cagrilintide here) slows gastric emptying, helps people feel full for longer (so the risk of binge-eating drops), and stabilizes glucagon levels. Anyone familiar with GLP-1 peptides like Semaglutide and Tirzepatide — and that’s everyone by now, right? — would be forgiven for asking the obvious. Novo Nordisk already developed Semaglutide. Why did the pharmaceutical giant go through the trouble of engineering yet another peptide that essentially has the exact same purpose?
That’s the right question to ask. Because it’s where things get interesting.
Semaglutide was a wild success that changed weight loss medicine forever. The obvious way to ride its coattails was this. Push the same target, the GLP-1 receptor, harder for more drastic weight loss results. The development of Cagrilintide results from a different question. “What’s next?”
Cagrilintide is an amylin analog. It indeed mostly does the same things GLP-1 peptides already do, but it uses a completely different pathway to induce weight loss. Instead of boosting the “I’m full” signal from within the gut (via GLP-1), it makes the pancreas send that message.
That opens up two particularly promising possibilities. The first is important and practical. If not everyone responds to Semaglutide and other GLP-1 peptides, or if some patients can’t take them, Cagrilintide is an alternative. More exciting? Multi-peptide treatment. Semaglutide and Cagrilintide, given together, could achieve more than either could on its own.
Obesity is a complex disease. Once it develops, the body defends it with all its might — using a network of redundant biological systems, it keeps fighting to hold onto or return fat stores. Attack it from one position, and it’ll try to find other ways to compensate. Start a full assault on all fronts, and the campaign can be more successful. Cagrilintide is far from “just another weight loss peptide.” It’s the compound that makes multi-peptide therapy possible.
A Very Brief History of Cagrilintide
Cagrilintide works very differently than Semaglutide and other GLP-1 peptides, but the Danish pharmaceutical giant that developed it still borrowed from its success when they decided to create a peptide that targets the amylin pathway. They used the same technique to make it long-acting — the single biggest ingredient in its success.
Amylin is a pancreatic hormone — the beta cells release it alongside insulin to manage blood glucose levels. Drawing out the amount of time you feel full (a brain thing) and the rate at which the stomach empties is part of its action. Important in its natural form and powerful as a treatment! Natural amylin gets released right after you eat something, and the action grinds to a halt mere minutes later, so that needed work.
A peptide called Pramlintide was the early result of that work — more long-acting than amylin, but still therapeutically annoying, it took three injections a day to maximize its potential.
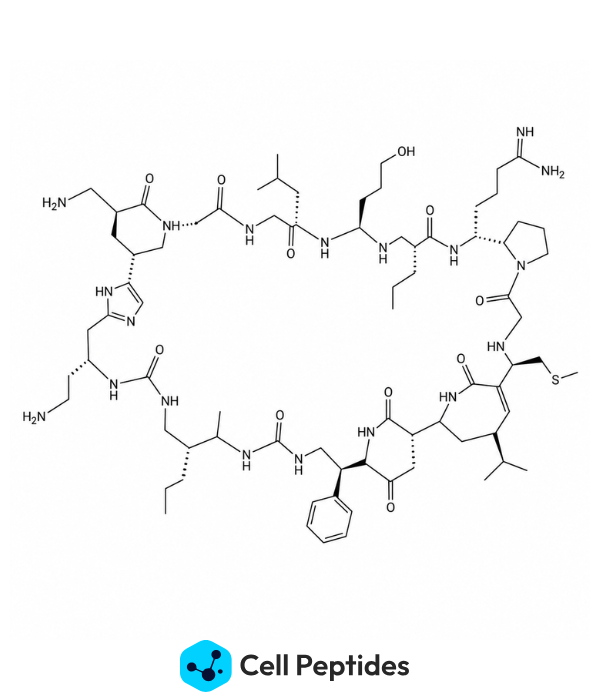
To make Cagrilintide, an amylin analog with a very convenient half life of seven days, the Novo Nordisk team attached a long fatty acid chain to the molecule they were working on — a mod that allowed Cagrilintide to bind to albumin. It’s the same tweak that made Semaglutide work. Albumin is a kind of bodyguard that stops the kidneys from degrading Cagrilintide. The result is the peptide used in research today. Scientists spent the 2010s working hard to prove its powers in preclinical research, and the first groundbreaking human trials were published in the early 2020s.
Cagrilintide isn’t quite as well known as Semaglutide yet, but that’s bound to change as research continues. The biggest potential is combination therapy — but that’s not all research is looking at.What’s the Mechanism of Action of CJC-1295 (no DAC)?
Nature’s way? The hypothalamus pushes out GHRH in short, rhythmic bursts — after which it makes its way to the pituitary and gets somatotrophs to make and send out growth hormone. CJC-1295 without DAC works identically. It gets a single strong GH pulse going and allows the pituitary to get back to its baseline. With a half life of about 30 minutes, CJC-1295 without DAC sticks around for much longer than natural GHRH — long enough to make it a powerful therapeutic, but not nearly long enough to start messing with physiological processes.
CJC-1295 without DAC is the “clean” way to boost natural growth hormone, and it has more potential applications than you might think.
Why Cagrilintide Matters
It’s already quite clear, from the human trials that were carried out, that Cagrilintide is an effective treatment for weight loss. Participants taking the highest dose are able to lose more than 10 percent of their starting body weights within 26 weeks [1].
That’s solid. It’s not also what makes Cagrilintide so promising, however. That part comes more from the “how” and “what next.”
Cagrilintide will continue to interest researchers because:
- Without it, the GLP-1 receptor risked staying the sole focus of weight loss drug development. Cagrilintide proves the amylin pathway works, that it’s just as important for metabolic regulation.
- Semaglutide has a good safety profile, but not all patients lose weight with it — and not everyone tolerates it well, either. People who tried Semaglutide (full of hope that it would be “the answer” only to find that it didn’t work for them might be in a minority, but they exist. Semaglutide is the clinically proven alternative that tells them not to give up on weight loss.
- Cagrilintide makes combination therapy possible. Cagrilintide and Semaglutide complement each other. They work together. The combination therapy CagriSema uses both — and that generally leads to more weight loss than either alone [2].
Weight loss isn’t the only research direction, either. Obesity and type 2 diabetes are inextricably linked — and across biological systems, too. Cagrilintide tames raging appetites, which happens in the brain. It makes patients feel full, which happens by keeping food in the stomach for longer. It also, on the other hand, smooths out blood sugar levels — preventing dangerous spikes. It’s an obesity treatment, yes, but this last effect shows it’s also a metabolic regulator.
The Most Important Findings in Cagrilintide Studies So Far (and What Could Be Next)
The last few sections might just have told you all you wanted to know about Cagrilintide — but if you’re still curious, you might want to know what specific findings have best showcased the potential this peptide has. The “headline” weight loss stats are impressive, but a deeper look demonstrates exactly what makes Cagrilintide so special.
The First Stage: Cagrilintide Proves To Be a Powerful Monotherapy Peptide
One of the studies you’ll see cited most often was a phase 2 human trial published in 2021 that investigated how effective Cagrilintide was at different doses — and that recruited participants from 10 different countries all over the world. This study lasted 26 weeks. Enough to give a very clear picture. [1]
The results were very far from ambiguous. People in the placebo group lost around and about two percent of their starting weights. At the lowest dose (starting with 0.3 mg), a weight reduction of around six percent emerged — already impressive. At higher doses starting with 2.4 mg, participants lost more than 10 percent. Double digits! This study proved that non-GLP-1 peptides could achieve the same kind of success in a completely different way. The amylin pathway works.
Better Results Together: Cagrilintide in Multi-Peptide Research
Once it was clear that Cagrilintide could achieve powerful weight loss results capable of competing with Semaglutide, it was time to move to bigger and better research — to see what was possible when Cagrilintide was combined with Semaglutide.
More than 600 studies have already been conducted into this combination therapy, and the findings are crystal clear. People given Cagrilintide + Semaglutide (CagriSema) lose more weight than obese patients treated with either alone. A 15 percent reduction in starting body weight is very realistic, studies and meta analyses show.[3, 4]
Makes sense — obesity is a whole-body disease, and targeting more than one pathway attacks it more effectively.
Tipping the Scale with Dramatic Metabolic Improvements — Cagrilintide in Diabetes Management
Like the other revolutionary weight management peptides that have become so popular recently, Cagrilintide effectively reduces body weight — but it’s a multi-tasker that also contributes to better metabolic regulation. Some studies have focused on Cagrilintide in isolation, but most now combine it with Semaglutide.
These studies show that Semaglutide + Cagrilintide as a combination therapy greatly improves glycemic control. They also provide evidence that Cagrilintide does a better job of reducing HbA1C than Semaglutide, but that the combination is even more effective.[2]
Cagrilintide has the potential to improve cardiometabolic markers like cholesterol levels and C-reactive protein, and because people given Cagrilintide in human trials consistently confirm that the peptide effectively reduces food cravings and appetite overall. [5, 6] Like Semaglutide before it, it’s far from only a weight loss treatment. Cagrilintide can hit the reset button on some of the metabolic changes a long struggle with obesity induces over time.
Safety and Side Effects
The many studies so far have also, of course, looked at the side effects that subjects treated with Cagrilintide report. So many phase 2 and 3 human trials have been approved precisely because the peptide has a good safety profile. It’s not without possible side effects — nausea, occasional vomiting, and diarrhea have all been reported — but patients generally report those when they start on the treatment, and note that they go away after a while. What’s also interesting is that far fewer people on Cagrilintide experience vomiting than with Semaglutide and Liraglutide. That means patients who stopped Semaglutide because of this side effect will have another option in Cagrilintide.[3]
Working with Cagrilintide: What Are the Most Common Delivery Methods?
With so many studies conducted to date, researchers designing protocols for Cagrilintide have a huge amount of data to draw from — both when it comes to dosing and delivery. The route of administration for Cagrilintide is already highly standardized. The peptide is delivered via subcutaneous injection.
This is non-negotiable for several reasons. SubQ delivery provides 100 percent bioavailability and makes sure the full dose is absorbed and circulated around the system. Cagrilintide was engineered specifically for this delivery route, and its slow release from subcutaneous tissues is what makes a once-weekly injection possible — convenient enough that patients can learn how to administer their prescribed treatment on their own, without having to go to the doctor every time.
Calculated Dosing Protocols for Cagrilintide Used In Research
With so many human trials under its belt, Cagrilintide is no longer a mystery. Optimal dosing protocols have well and truly been established for weight loss contexts.
Trials slowly escalate the dose to give participants time to “get used” to the treatment and observe how they respond — in steps. Many:
- Start with 0.3 mg
- Move up to 0.6 mg
- Continue with 1.2 mg
- Finally reach the target dose of 2.4 mg
Studies might run for 26 weeks or longer.
The biohacking space also brings useful anecdotes, and researchers here tend to be more conservative with dosing. It is not uncommon to read about protocols that start with 200 to 300 mcg (0.2 to 0.3 mg), escalate in increments of 0.1 to 0.2 mg per week, and end with 0.75 mg. The idea here is to start low and go slow. Researchers here also observe how the model responds, and may move up to the dosage tested in clinical trials if Cagrilintide proves to be well tolerated.
Obligatory disclaimer: This section is here to give you a better idea of how researchers in all fields have worked with Cagrilintide. It’s not medical advice, and it’s not research design guidance, either.
FAQs
Semaglutide works mainly in the gut area. It impersonates GLP-1, which tells your brain you’re full after eating and keeps food in the stomach for longer. Cagrilintide is an analogue of the amylin produced in the pancreas. Its main effects are very similar, but the way it achieves them is different. That’s why Cagrilintide is promising — for people who can’t take GLP-1 peptides or don’t lose weight on them, and as a combination therapy.
Not quite yet, but phase 3 trials are well underway and clinical use is likely not that far off.
Cagrilintide has a half life of six to eight days. That’s what it was designed for — a long-acting, extended-release peptide is convenient for patients.
The highest dose studied consistently leads to losing around 10 percent of subjects’ starting weights in around 26 weeks. As one part of Cagrilintide + Semaglutide therapy, that result jumps to 15 percent — and it takes less time to achieve it.
Scientific References and Sources
- https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(21)01751-7/abstract[↩][↩]
- https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(23)01163-7/abstract[↩][↩]
- https://journals.lww.com/indjem/fulltext/2024/09000/efficacy_and_safety_of_cagrilintide_alone_and_in.2.aspx[↩][↩]
- https://www.nejm.org/doi/abs/10.1056/NEJMoa2502082[↩]
- https://onlinelibrary.wiley.com/doi/abs/10.1002/j.2040-4603.2020.tb00140.x[↩]
- https://www.mdpi.com/2673-4540/4/3/24[↩]